


Family caregivers deserve care too
Family caregiving is one of the hardest jobs a person can take on. Every day, millions of people step into the role of caregiver for a parent, spouse, child, sibling or other loved one. They manage appointments, coordinate care, keep track of medications, assist with daily activities, provide emotional support and so much more. They do it out of love, a sense of responsibility and a desire to help someone they care about live a healthier, more comfortable life.
And often, they do it without pay, without formal training and with very little recognition.
Approximately 63 million Americans provide ongoing care to an adult or child with complex health needs. That’s as many people as the entire states of Illinois, Ohio, Michigan, Indiana, Missouri, Wisconsin, Minnesota and Kansas.
The 2025 Caregiving in the U.S. report highlights the emotional toll of caregiving: 64% of caregivers experience emotional stress and nearly one in four feel alone. But 51% say caregiving gives them a sense of purpose.
Caregiving can be both deeply rewarding and incredibly demanding.
Love can mean taking responsibility
Why do people take on such a challenging role? For many, the answer is simple: they have no other choice. Family caregivers frequently step into their role due to a lack of financial, institutional and community resources.
But for many, it also comes down to giving back to someone who once cared for them. They love this person and feel a duty to them. They want to keep their loved one safe and comfortable at home and also feel a responsibility to be there when someone needs them most.
Caregiving can bring a tremendous sense of purpose, pride, connection and fulfillment. But those positive feelings often co-exist with worry, exhaustion, guilt, frustration and loneliness. Caregivers often say they struggle to balance their responsibilities with careers, parenting, relationships and their own health.
Over time, the demands can become overwhelming. And because caregiving often happens behind closed doors, the sacrifices can go unnoticed by everyone except the person doing the work.
Family caregivers need care and support too
The good news is that caregivers don’t have to navigate this journey alone. There are resources available to help ease the burden, provide temporary relief and connect families with financial and community support.
Here are a few places to start:
- Respite care: The Eldercare Locator (800-677-1116) can connect caregivers with local Area Agencies on Aging that can help find respite care, adult day programs, support groups and other services. The ARCH National Respite Network can be another resource for finding temporary care.
- Financial assistance: Some states offer Medicaid programs that may compensate eligible family members for caregiving. USA.gov’s caregiver assistance guide has a good explanation of options, including Medicaid self-directed programs, paid family leave and veterans’ benefits.
- Caregiver support and education: The Administration for Community Living’s National Family Caregiver Support Program can offer access to counseling, caregiver training, support groups, respite care and supplemental services through participating state and local programs.
- Veteran caregiver support: The VA Caregiver Support Program can offer eligible caregiver education, counseling, respite care and, for qualifying caregivers, financial assistance.
Technology can never replace human care, but it can help make certain caregiving responsibilities more manageable.
Managing medications is a vital and often stressful part of caring for a loved one. Keeping track of multiple prescriptions, schedules and doses can add another layer of responsibility to already busy days.
That’s why Ōmcare is committed to helping families with solutions that support medication adherence. The Ōmcare Home Health Hub simplifies medication routines, provides added support and gives caregivers greater peace of mind. It’s one more way technology can help support the people who do so much for others.
Giving thanks
Family caregivers don’t necessarily ask for applause or recognition. They show up because someone they love needs them. Caregivers deserve to know their efforts matter and need time to rest, resources to help and support that acknowledges the enormous responsibility they carry.
This Family Caregivers Month, do more than say thank you. Check in on a caregiver, offer to help with an errand, give them a much-needed break or simply remind them that they’re not alone.
To every family caregiver: Thank you for all that you do. You spend so much time caring for others and this month, we celebrate you.


Seniors: Live where you choose, longer
Seniors: Live where you choose, longer
By Lisa Lavin, CEO
At Ōmcare, our mission is to help people over age 65 live where they want to live, longer. It’s in all our material and in conversations with clinicians and partners. It is central to everything we do.
But a phrase you repeat every day can quietly lose its meaning. So, I’ve been asking myself a simple question: What does living where you choose, longer, actually mean to the people living it?
Here’s where I’ve landed. It’s not a policy term, it’s just life.
It’s the life someone has built and is continuing on their own terms. It’s their kitchen that they know by heart, the neighbor who waves from the porch each morning, the Tuesday coffee group and the garden that always needs tending. It is dignity, choice, routine, connection and independence, held together for as long as possible.
What people tell us they want
The desire to stay home isn’t a niche preference, it’s nearly universal.
At least 75% of adults 50 and older said they want to remain in their current home as long as possible, and 73% want to stay in their community, according to AARP’s 2024 Home and Community Preferences Survey.
That desire is even stronger among people age 65 and older and also for those living in small towns and rural areas,
But what jumps out at me most is the gap between someone wanting to remain in their home and being ready to actually do that. In that same survey, 43% said they’d need to modify their home to keep living there and 64% said they want a medical emergency response system.
People aren’t asking to be rescued, they’re just asking for a little help maintaining stability.
Five words that matter
When you ask people what living where they choose means to them, five motivations usually come up. And each one looks very different in a real home.
Dignity
A retired schoolteacher managing her own heart medications instead of having a stranger count pills into her hand. It’s being trusted with your own life.
Choice
The 84-year-old man who remains in his home, adapting it to his needs, rather than moving somewhere else. Good care bends to the person, not the other way around.
Routine
The morning coffee, the crossword and the daily walk to the mailbox. For many older adults, especially those living with early memory changes, routine isn’t just a habit. It’s the scaffolding that keeps the day standing.
Connection
The daughter three states away who gets a quiet reassurance that Mom took her medication, so their nightly call can be about the grandkids instead of a health checklist.
This is a big one. Social disconnection raises the risk of premature death to a level comparable to smoking up to 15 cigarettes a day, according to the U.S. Surgeon General’s 2023 advisory. That isolation among older adults drives an estimated $6.7 billion in excess Medicare spending every year.
Independence
The widow who can still live alone in her home because the smaller risks like a missed medication dose, a fall or a night when something feels off are covered by a safety net she barely notices.
Technology to support, not replace
Ōmcare focuses on medication adherence. Here’s why it matters:
Roughly half of patients with chronic conditions don’t take their medications as prescribed.
In the U.S., nonadherence is associated with about 125,000 deaths a year, at least 10% of hospitalizations and $100 billion to $300 billion in avoidable spending per year.
Physicians often treat medication nonadherence as a patient problem rather than a health-system problem, researchers have noted.
Behind those numbers are ordinary and very real moments.
A dose missed because the label was confusing.
A pill taken twice because yesterday blurred into today.
A refill missed because the pharmacy is 40 minutes away and the roads iced over.
Each one could be relatively small, but together, they are often the difference between staying home and moving out.
This is where technology can shine. It can offer a reminder that arrives at the right moment, a dispenser that makes the right dose easy and the wrong dose hard and a gentle alert to a family member or nurse when something is actually off.
Done well, none of this feels like surveillance, but more of a steady hand.
To be clear: Technology cannot and should not replace human care. A device can tell a nurse that a dose was missed, but it can’t ask why, notice the grief in someone’s voice or sit at the kitchen table and listen. The best health technology quietly helps people live the lives they already want, and it makes the humans in their lives more effective, not less necessary.
Rural America: where staying home is hardest
For anyone who needs a demonstration of what living where you choose truly asks of us, visit rural America. About 15% of Americans overall live in rural counties, but 22% of Americans over age 65 live in rural areas.
At the same time, the care around them is evaporating. Since 2010,182 rural hospitals have closed or stopped offering inpatient care. That is roughly 10% of the nation’s rural hospitals. Nearly half (46%) now run at a negative operating margin and at least 432 are considered vulnerable to closure.
For an older adult in a small town, that math is personal. It means a longer drive to a pharmacy and even further to get to a pharmacist who knows your name when they see you.
It means a home health nurse covering an entire county instead of a neighborhood and family caregivers stretched across distance and jobs. In these places, a missed dose or an unnoticed decline isn’t a minor event. It can be the first step toward permanently leaving home.
That’s exactly why rural communities are where thoughtful technology can do the most good. However, tools built for a city apartment with fast wi-fi and a clinic right down the block won’t always work reliably for a farmhouse at the end of a gravel road. Rural seniors deserve technology designed for their reality.
What policy can do next
We’re at a rare moment for rural health. The federal Rural Health Transformation Program is distributing $50 billion to all 50 states over five years, $10 billion a year from 2026 through 2030, with first-year awards ranging from $147 million to $281 million. Its stated goals include expanding access, strengthening the rural workforce and modernizing technology and care models. Provider groups have welcomed the funds while cautioning that they don’t offset projected Medicaid reductions in the same law.
How states spend this money will shape rural aging for a generation. At Ōmcare, we believe a few principles should guide it:
- Measure success by days at home. Fund programs by whether they help people stay safely in their own homes and communities, not only by the number of devices deployed or visits logged.
- Pay for the human-plus-technology model. Reimbursement should reward nurses, pharmacists and community health workers who use remote tools to reach more people, so technology extends caregivers rather than replacing them.
- Design for rural from the start. Require that funded tools work on limited broadband, are easy for people with low vision or arthritis to use and are tested with rural older adults themselves.
- Treat medication management as core care. Adherence support is one of the most direct, measurable ways to prevent avoidable hospitalizations. It should be centered in state plans, not on the margins.
- Support family caregivers. They are the backbone of helping people live where they choose. Give them training, respite and tools that reduce worry rather than add another app to check.
I believe industry leaders have a responsibility to bring what we see in real homes into policy conversations honestly and with older adults at the center of the table.
Back to the kitchen table
“Live where you choose, longer” is the phrase I’ll keep saying, because it names what the people we serve actually want. And I try to hear it the way they live it: as the morning coffee, the garden, the neighbor’s wave and the right to decide for yourself how your days unfold.
Our job in technology, in care and in policy isn’t to redesign lives. It’s to protect them, quietly, and for as long as possible. If we get that right, the best compliment our work can receive is that people barely notice it’s there.

Why medication adherence is bigger than a pill
Why Medication Adherence Is Bigger Than a Pill
By Lisa Lavin, Ōmcare founder and CEO
Healthcare has a tendency to measure what happens at the point of care.
Did a patient take their medication? Did the numbers improve? Did they avoid the hospital?
But some of the most important outcomes happen much farther downstream.
As poet Seamus Heaney described, “I have begun to think of life as a series of ripples widening out from an original center.”
That is what makes medication adherence so powerful. And so easy to underestimate.
I think about the children’s book If You Give a Mouse a Cookie. One small action sets off a chain reaction: give the mouse a cookie, and suddenly he needs a glass of milk, then a straw and so on…
Medication adherence can work the same way. Except the ripple isn’t a storybook chain, it’s a human one.
When an older adult takes the right medication, at the right dose, at the right time, consistently, the impact can extend far beyond that single dose.
Better medication management can help someone remain stable. Stability can mean fewer complications and avoidable hospitalizations. Fewer hospitalizations can mean fewer setbacks to strength, mobility and function.
And function is about much more than health.
- It is the ability to get out of a chair without help.
- To make your own breakfast.
- To walk into your own kitchen.
- To stay in the home you’ve lived in for decades.
- To remain connected to your community.
- To preserve a sense of independence and dignity.
For a family member, it can mean fewer late-night calls and fewer hours spent wondering whether Mom or Dad took the right medications.
For a caregiver, it can mean less time managing pill boxes and medication schedules and more time simply being a daughter or son, a spouse or a friend.
And in rural communities, where healthcare resources can be stretched thin and a trip to a specialist, clinic or hospital can mean significant distance, these ripples can matter even more. Keeping someone healthier and more stable at home isn’t just convenient; it can help bridge the distance between people and the care they need.
I believe this is where the future of healthcare is headed.
We cannot build a sustainable healthcare system around constantly reacting to crises. We need to move upstream and identify risk earlier, support people between appointments and give caregivers and care teams the tools to intervene before a manageable problem becomes an emergency.
Medication adherence is one of those upstream opportunities.
- When patients are more stable, clinicians have more capacity to focus on proactive care.
- When caregivers have better support, they can spend less time coordinating medications and more time caring for the person they love.
- When technology connects patients, caregivers and providers, care doesn’t have to stop when the appointment ends.
That is the opportunity in front of us: not simply to help people take their medications, but to use medication management as a gateway to a more proactive, connected model of care.
Technology should not replace human care; it should instead extend that care.
It should help a nurse see the signal before the crisis, a caregiver know that something has changed, an older adult remain confident in their own home and a rural patient stay connected to the healthcare system without every problem requiring a long drive or a hospital visit.
Ultimately, technology should give people more of what healthcare is supposed to protect: time, independence, dignity and the ability to live their lives on their own terms.
That’s why we at Ōmcare think differently about what we’re building.
We aren’t just solving for a missed dose; we’re solving for everything that can happen when the right dose isn’t missed.
The smallest intervention can sometimes create the largest ripple, and that ripple can begin with something remarkably simple:
- The right medication
- At the right dose
- At the right time
- Consistently
That is why we do what we do.

When the clinic closes, can in-home pharmacy help? Silver Bay, Minnesota is about to find out
On the crisp, sparkling shores of Lake Superior on Minnesota’s North Shore, Silver Bay is more than a city, it’s a lifestyle. About 1,800 people call it home, drawn by the views and the peace of small-town life.
But, like many rural communities across the country, Silver Bay has been losing vital healthcare access with residents facing increasing barriers to getting care.
The city’s only healthcare clinic is closing in December 2026 and nearly a third of residents are 65 or older. That’s exactly the population that feels a healthcare gap the most. The town’s only pharmacy is not open on weekends and residents will now need to transport at least 30 miles away for clinical and emergency services.
That has left many people wondering how they’ll be able to stay independent at home in Silver Bay.
Now Silver Bay is stepping up as the second Minnesota community to join the Rural Health Innovation Initiative, a six-month pilot led by the University of Minnesota Center for Healthy Aging and Innovation. The goal is to test the impact of pharmacy and care services delivered directly into people’s homes, no matter how far they live from the nearest pharmacy.
One countertop device opening a world of services
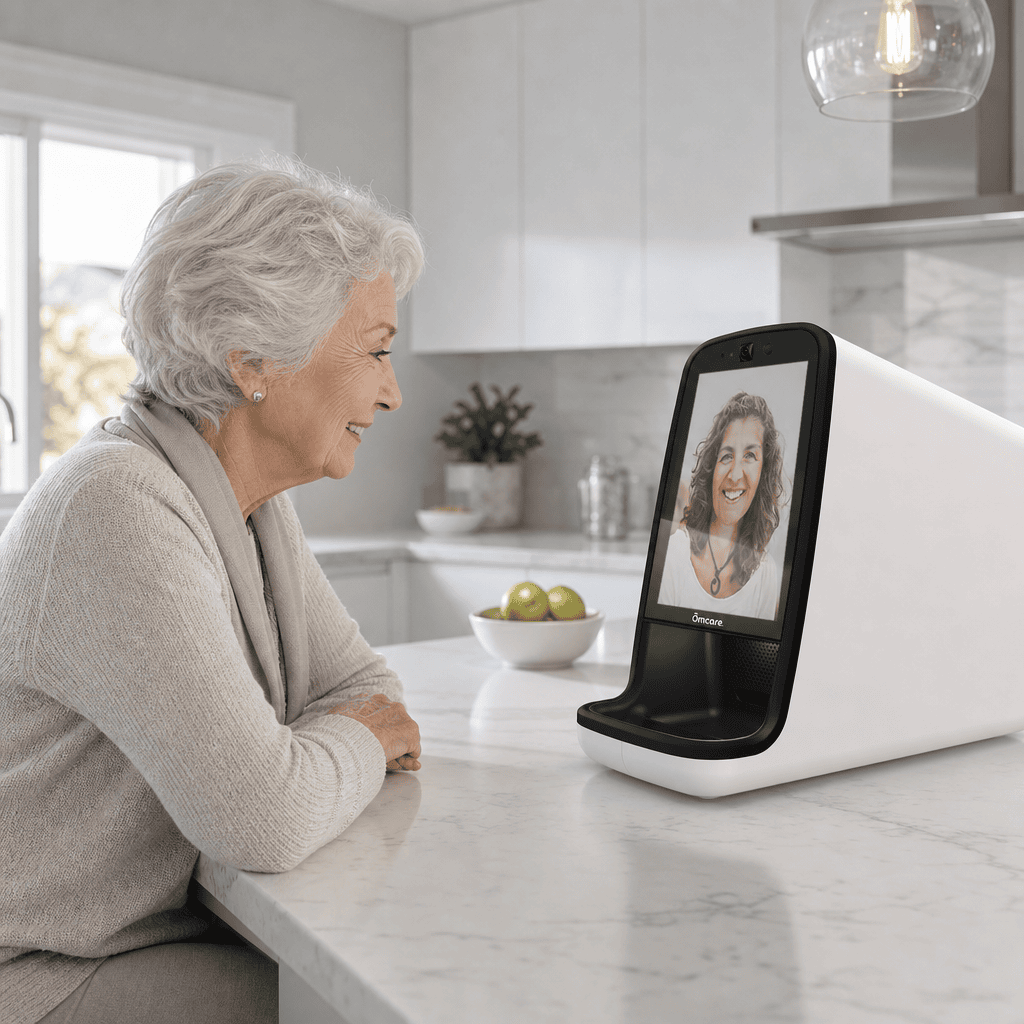
The centerpiece of the pilot is the Ōmcare Home Health Hub®, a compact in-home device that automatically sorts and dispenses medication in pre-timed packets whenever a person’s medication schedule calls for it. There’s no more guessing whether today’s pills were taken.
Beyond medication management, the Hub gives participants:
- A screen for video calls with family, friends and caregivers
- 24/7 phone access to pharmacy staff
- Monthly check-ins with a medication management team
It’s built to answer a simple but urgent question: can older adults get consistent, reliable care without living close to a pharmacy?
Local leadership sees an opportunity
Silver Bay Mayor Wade LeBlanc has been vocal about what this pilot could mean for the city’s future. As a small community working to support its aging population with a thinning healthcare infrastructure, he sees real potential in bringing this kind of innovation home. And he’s hoping it sticks around.
The city is already looking past the six-month pilot window, aiming to partner with Essentia Health to keep the service model in place for residents long-term.
The view from Ōmcare
This isn’t about any one device; it’s not technology for technology’s sake. This pilot is about communities people are committed to staying in, even with the erosion of the infrastructure that once supported them.
Silver Bay reflects exactly the kind of community the pilot was built for. It’s a town people love deeply, where they want to spend their entire lives, but where the healthcare system hasn’t kept pace.
For us, the pilot is a chance to test whether an in-home model can genuinely close that gap, not just patch it, to help residents stay healthy, independent and connected to the community they’ve chosen.
It’s easy to think of a medication management as a logistics problem to solve. But the connection achieved through check-ins with family, loved ones and caregivers is just as important. Isolation is as much a rural health risk as a missed medication dose, and worth designing for.
Why this matters beyond Silver Bay
Silver Bay isn’t an outlier. Rural clinics and pharmacies have been closing across Minnesota and the country for years. The communities left behind are disproportionately older. The Rural Health Innovation Initiative is explicitly designed to test whether the Ōmcare model can scale; not just as a stopgap for one North Shore city, but as a blueprint for rural communities nationwide facing the same erosion of local care.
The University of Minnesota Center for Healthy Aging and Innovation is leading the evaluation and tracking outcomes over the six-month pilot to understand how well the model supports aging in place. It’s all part of discovering what it will take to bring it to more towns like Silver Bay.
Is your community next?
If your rural community is watching its local healthcare options shrink, this pilot might be worth a conversation. Communities interested in bringing this kind of in-home medication management and care model to their own residents can reach out to the University of Minnesota study office to learn about participating in a future pilot.
Ready to explore what this could look like where you live? Contact Email: healthstudy@umn.edu


Experiencing one life
by Lisa Lavin, CEO, Ōmcare
Care for older adults was built around systems, not really around the realities of how individuals and their caregivers actually live. Not only can those realities change for people, as the older adult population grows, caregiver capacity shrinks, healthcare costs rise and people live longer with multiple chronic conditions … doing more of the same thing isn’t enough.
Older adults don’t experience healthcare as a collection of systems
Every time an older adult interacts with:
- Primary care providers
- Specialists
- One or more pharmacies
- Home health providers
- Hospitals
- Insurance companies
- Transportation services
- Family caregivers
They encounter different processes and priorities.
Seen from 10,000 feet, these are collections of systems, but adults ages 65+ are experiencing one life.
If those systems aren’t connected or aren’t willing to try new approaches, the burden of coordinating everything falls on the individual or their family caregiver. That’s especially problematic when someone is managing multiple medications, appointments, diagnoses, mobility challenges and/or cognitive changes.
Instead of expecting older adults and caregivers to continually navigate these systems, we have the opportunity to bring support closer to the person’s actual day-to-day life.
Keeping people at home needs to be more than just a slogan
Most care organizations want the same outcome: help people remain independent and healthy in their homes for as long as possible.
But achieving that requires asking a different question: What does this person need between healthcare visits to actually make that possible?
- A 15-minute visit with a physician
- The every day routine of a family caregiver managing medications
- 8:00pm on a Sunday when someone is struggling to remember if they took their medications on time
- A brief home care visit where a care worker sees warning signs
In that space between those experiences there is enormous opportunity.
Technology, remote monitoring, medication management, community services, home-based care and new models of caregiver support can help fill those gaps.
Crisis prevention is better than crisis management
When something goes wrong, our healthcare systems are very good at responding. But for adults over age 65, relatively small problems can quickly become big.
One missed pill, dehydration, an untreated infection, a fall or a caregiver becoming overwhelmed can quickly result in an ER visit or hospitalization.
Technology and willingness to innovate gives organizations more opportunities to identify problems earlier and to intervene before they become crises.
That’s not just better healthcare, it’s better quality of life. And often less expensive than repeatedly treating preventable complications.
It’s time to embrace familial caregivers as an official and vital part of the care team
Family caregivers are often doing an enormous amount of invisible healthcare work.
- Organizing medications
- Driving to appointments
- Communicating with providers
- Watching for changes
- Managing meals
- Coordinating services
- Calibrating whether something is “normal” or if they should call in higher level assistance.
If organizations design care without considering the caregiver, they’re leaving out a huge and vital piece of the care puzzle.
Meeting older adults where they are also means meeting caregivers where they are. This can mean:
- Providing better and more clear information
- Reducing coordination burdens
- Providing tools that give them confidence that something has been completed and correctly
- Allowing technology to extend the reach of already-overstretched professionals
Innovation doesn’t have to mean throwing everything out and starting over
Being open to innovation doesn’t mean abandoning proven practices or adopting every shiny new technology. It means being willing to ask:
“Is there a better way to accomplish the outcome we’re already trying to achieve?”
Sometimes the answer will be no. Sometimes an existing process is genuinely the best one.
But organizations can become so accustomed to how something has always been done that the process accidentally becomes confused with the goal.

There doesn’t need to be a solo solution
Organizations: You don’t have to solve every problem internally.
Service organizations, health systems, home care agencies, pharmacies, technology companies, community organizations and caregivers are all unique pieces of the puzzle.
The strategy that benefits everyone is willingness to collaborate and let others bring new capabilities into the ecosystem.
The question doesn’t have to be: “Is this our solution?”
It can be: “Does this help our older adults and their caregivers achieve the outcome we’re all working toward?”
In fact, that’s a much more productive way to think about innovation.
The bigger idea
Ultimately, innovation in older adult care isn’t just about technology, it’s about willingness to change the way we all deliver support when the old way isn’t working well enough.
Older adults deserve care that fits into their lives rather than contorting their lives to fit into the healthcare system. Caregivers deserve support that recognizes the enormous role they’re already playing. And healthcare and older adult-service organizations need enough flexibility to experiment, collaborate and adopt new approaches when those approaches can improve outcomes.
The organizations that are willing to do that aren’t abandoning the system. They’re protecting its purpose.
The goal we’re all working toward? Helping older adults live healthier, safer and more independent lives at home. With this in mind, being open to new ideas should not be seen as a disruption of the mission, it’s all in how the mission is fulfilled.
If your organization is ready to reduce hospital readmissions and improve medication adherence rates, let’s explore a partnership.
The missed opportunity in home care: How medication management unlocks new revenue without more staff
Shanna Eckberg isn’t new to aging services. She’s worked in senior care since she was 16, starting as a dietary aide, moving through accounting and operations, earning her nursing home administrator license and eventually serving as CEO.
In 2025, she launched Syncara, LLC, her own home care company to focus on one goal: helping older adults age the way they choose, using technology to fill growing gaps in care.
When she first saw the Ōmcare Home Health Hub®, the value was immediate.
“I remember thinking, where were you two years ago?” she laughs. “This tool can help us watch clients take their medications so my team can focus on other care.”
The Ōmcare Home Health Hub® dispenses pharmacy-prepacked, reconciled medications at the right dose and time, without requiring a nurse to load pillboxes. Agencies can monitor adherence virtually, support clients discharged with any number of medications and provide peace of mind to families.
“Why not offer an option that doesn’t require much caregiver time in the home, but can still provide a quality service, build trust and generate additional revenue?” Shanna asks.
However, for many home care executives, new technology raises a fair question: Is this going to take away our business?
Shanna understands that concern. And she challenges it.
“It gives our agencies another opportunity to meet needs creatively by offering services in the home without requiring a lot of staff time.”
For home care agencies facing staffing shortages and rising demand, medication management isn’t a replacement for care, it’s a new front door into a home, creating earlier relationships and sustainable growth without adding overhead.

Key takeaways for leadership
- Medication management is now a core business risk and opportunity
- Public-private collaboration is the future of rural aging support. The healthcare system needs home care providers as core partners. Agencies willing to pilot innovation and collaboration can move ahead of competitors. This is not just a shift in care models, it’s a new ecosystem forming around aging-in-place.
- Home care must step into healthcare’s gap. Rural markets need new partnerships and technologies to fill widening healthcare gaps. Home care is positioned to lead.
“I feel we are on the edge of something great. Having an open mind is crucial to our successes as providers.”— Shanna Eckberg, CEO, Syncara

How to take medication management from cost center to profit center
Most home care agencies treat medication management as a task. The ones that operationalize it as a service line will see measurable gains in margin, differentiation and enterprise value.
Despite dealing with tighter margins, staffing shortages and the shift to value-based care, there’s a practical way for home care agencies to improve outcomes and the bottom line that often gets overlooked: medication management.
Summary for business leaders
- Medication non-adherence is quietly eroding your margins
- Most clients manage between five and 10 (or more) medications. Missed doses and medication errors drive avoidable hospitalizations, liability risk and caregiver inefficiency.
- Your current approach is not scalable
- Pill boxes, reminders and caregiver oversight depend on consistency. And you can’t guarantee that at scale. Your highest cost clients are also the hardest to manage. And the most expensive when things go wrong.
- The opportunity is targeted, not universal
- Only about five to 10 percent of clients require advanced medication management. Focusing on this high-risk segment delivers disproportionate financial and clinical impact.
- Med management tech is not just cost-control, it’s a revenue engine
- Medication management technology can add between $300-$1,500/client/month in new, recurring revenue. Additionally, organizations realize reduced caregiver burden, better labor utilization and fewer costly medication errors which can cost $3,000 to $4,000 per incident.
- Med management tech is a strategic lever for growth and differentiation
- Medication management technology allows you to engage clients earlier and increase lifetime value, strengthen family trust and retention and create a platform to layer on higher-margin services over time.

For organizations moving toward value-based care, the opportunity is clear: focus on high-risk clients and support them with technology like the Ōmcare Home Health Hub. This isn’t about a system-wide rollout, it’s about being precise and intentional where impact is highest.
Leading home care organizations are no longer treating medication management as a task, they’re incorporating it as core infrastructure for growth and margin improvement.
Ōmcare helps you deploy faster, operate more consistently and capture both clinical and financial upside sooner.
Medication management isn’t just a clinical need, it’s a business opportunity hiding in plain sight. Explore Ōmcare’s Medication Assistance Service.

The last mile in value-based care: closing critical gaps between healthcare facilities and home
“We believe there is a not-so-distant future when medication non-adherence becomes a far more manageable issue.” – T.J. Griffin, Chief Clinical Officer, PharMerica
As seniors and rural patients face increasing mobility challenges, pharmacy and hospital closures and complex medical regimens, all of that (and more) is becoming the reality for those in value-based care.
- Avoidable utilization
- Rising mortality risk
- Fragmented care delivery
- Weakened performance in value-based models
It’s a no-win reality: seniors facing declining access and outcomes, rural communities left with fewer care options and healthcare organizations asked to deliver better results with fewer touch points and shrinking infrastructure.
Patient isolation and the “last mile” of medication management are where these challenges become system-level risks.
But they also represent a system-level opportunity.
A model built for scale
A new public-private Rural Health Innovation Initiative is focused on delivering pharmacy services, virtual care and medication management directly into homes.
The initiative is driven by Ōmcare, PharMerica , Mayor Alicia Pearson of Lanesboro, Minnesota and the University of Minnesota Center for Healthy Aging and Innovation, all committed to extending care beyond traditional facilities while maintaining quality, continuity and accountability for seniors and rural populations.
Why it matters to you

Key takeaways for value-based care leaders
- Acting now can stabilize rural access. With rural hospitals under financial strain and service lines disappearing, healthcare organizations must proactively extend care into the home to prevent gaps in access and continuity.
- Home-based pharmacy and virtual care are essential. Mobility barriers and medication complexity are driving avoidable utilization. Pharmacy-to-home and virtual care models directly improve adherence and outcomes.
- It’s possible to scale without new facilities. Technology-enabled medication management and remote care allow organizations to expand reach in low-density regions without significant capital investment.
- Connected-care data can be used to drive transformation. In-home care models generate continuous clinical and behavioral data that support early intervention, population health analytics and system-wide improvement.
“What can we do to bring healthcare back to rural America? We know we must approach it differently, and we recognize that change is never easy. For generations, these communities have endured, but endurance alone is not enough. Together, through public-private collaboration, we have the opportunity to make a real difference and improve lives across rural America.” – Lisa Lavin, CEO, Ōmcare
Explore how the Rural Health Innovation Initiative can strengthen your organization’s rural footprint, improve adherence and close the last-mile gap dragging down value-based outcomes.

The pill puzzle: Why current medication adherence isn’t enough
Around 125,000 deaths each year in the US are due to prescription medication non-adherence. The term – adherence – refers to following physicians’ prescription drug instructions to patients in treating their disorders. While a reported 50% of all patients struggle with medication adherence, this problem is even worse in seniors. One reason is a lack of understanding for the need to take a particular drug, but another is forgetfulness. However, that forgetfulness is most often related to taking multiple daily medications and mixing them up. Regardless of the specific reason for stopping a medication, confusion over when to take it, or never taking it at all, a chronic health disorder is likely to worsen as a result.
Prescription medications used to treat cancers: Why adherence is necessary
Oral chemotherapy pills that can be taken at home are replacing intravenous (IV) chemotherapy delivered in treatment centers for many patients. Four types of cancer that can now be treated by taking daily oral chemotherapy medications are:
- Leukemia
- Breast cancer
- Prostate cancer
- Renal cancer
According to the National Cancer Institute (NCI), half of all cancers occur in people aged 66 and older. Likewise, the NCI notes that senior age is the most important (overall) risk for cancer, with the median age linked to the following cancers:
- Breast cancer – median age at diagnosis: 62 years old
- Colorectal cancer – median age at diagnosis: 67 years old
- Prostate cancer – median age at diagnosis: 66 years old
When chemotherapy pills are suddenly discontinued or taken incorrectly, the cancer tumors can return or grow. An article in the Journal of Oncology Practice reported that three other consequences of chemotherapy pill nonadherence are increased use of healthcare resources, higher hospitalization rates, and longer inpatient stays. Especially for seniors with cancer, longer hospitalizations are linked to developing hospital-acquired infections.
Diabetes medication adherence in seniors and nonadherence consequences
At least 16.5 million adults aged 65 and older in the US are living with Type-2 diabetes, and many take oral prescription medication to control it. When the daily pill to control blood glucose level is skipped or taken at the wrong time of day, there is a far higher likelihood that diabetes complications will develop. These complications include neuropathy (nerve pain), heart disease, and kidney failure.
What is polypharmacy and why does this lead to medication nonadherence?
Polypharmacy is the term used to describe taking more than five different prescription drugs each day. Problematically, polypharmacy was reported in up to 39% of all adults aged 65 and older (per an article in Global Health Research and Policy). Meanwhile, short-term memory problems increase with aging. Therefore, the pill puzzle can become highly complex for seniors as they age. Since adults are living to much later ages than ever before, the generally low level of prescription medication adherence among adults needs to be increased. Otherwise, a lower overall quality of health after age 70 may be the consequence.
Digital devices, like the Ōmcare Home Health Hub® make guessing a thing of the past with medication reminders and one-touch access to video conferencing, guaranteeing right med, right time, right person every time.

The adherence advantage: Unlocking the benefits of enhanced medication adherence
Taking medications as prescribed is something that is not as easy as it sounds. This is especially the case for seniors, who may take several prescribed drugs each day. It really is vital to recognize that non-adherence can mean not taking a prescribed drug at all, or it can mean taking it but mixing up the dose or time of day to take it. The following describes what can happen if you do not take specific prescription drugs as prescribed, as well as the benefits of medication adherence to treating three common health disorders in seniors.
Lack of medication adherence in seniors with high blood pressure: Why it matters
Around 60% of all adults in the US by age 60 have high blood pressure (hypertension). This percent increases with age. Meanwhile, high blood pressure is the leading cause of strokes. Certain medications are prescribed to ensure that blood pressure remains within a normal range in adults living with chronic hypertension. In this way, a stable blood pressure is maintained, so as not to be too high or too low.
When a person skips a daily blood pressure medication, the result can be a dangerous spike in blood pressure. However – if a morning dose is taken instead at bedtime – the person could arise to use the bathroom, but then faint due to an overly-low blood pressure. This is because it can take several hours for an oral blood pressure drug to work as intended.
Medical researchers have determined that adults who are non-adherent to prescribed drugs to control hypertension are nearly six times more likely to have a stroke than those who are adherent. Since strokes often cause permanent disability in older-aged adults, adhering to blood pressure drugs can be imperative to future overall health and well-being.
The benefits of medication adherence for managing diabetes-type 2
At least 29% of all adults aged 65 and older are living with Diabetes-Type 2, per the Centers for Disease Control. While insulin is the standard treatment for Diabetes-Type 1, prescribed pills of antihyperglycemic drugs are the standard treatment for Diabetes-Type 2. These daily antihyperglycemic medications help to maintain the blood sugar level within normal range. If not taken each day (or not taken at all), the blood sugar level can remain too high or even increase.
Uncontrolled or poorly-controlled Diabetes-Type 2 can boost the likelihood of developing many of the common diabetes complications. These complications include:
- A type of nerve pain in the limbs called peripheral neuropathy
- Heart disease, resulting in an increased risk of heart attacks
- Blindness due to diabetic retinopathy
- Transient Ischemic Attacks (TIAs)
- Kidney damage
Benefits of medication adherence for controlling cholesterol level
High cholesterol increases the risk for a heart attack. According to the American Heart Association, the main reason is that too much cholesterol in the bloodstream causes fatty deposits (plaques) to form in the artery walls. In turn, the plaques can break off, travel in the bloodstream toward the heart as a clot, and then block blood-flow to the heart.
The FDA approved the first statin drug to lower cholesterol in 1987. Since that time, statins have been prescribed by doctors to many millions of adults to lower cholesterol. This is because taking a daily statin drug has been shown to tremendously lower heart attack risk in adults with chronically-high cholesterol. However, statin medication needs to be taken daily for life after beginning its use. Otherwise, cholesterol level is likely to spike back up.
Heart disease is the leading cause of death in adults in the US, and especially in senior-aged adults. Therefore, medication adherence to a prescribed statin drug by an adult diagnosed with high cholesterol can be life-saving.
How smart technology can increase medication adherence in seniors
Having a family member or friend remind a senior-aged person to take daily prescribed medications every day can be effective at increasing medication adherence to prescribed drugs. However, this is not a realistic solution in most cases, as even a family member or friend can forget to tell the senior-aged person every day to take the prescribed medication. Fortunately, there now are apps and other mobile devices that enable users to set reminders.
Meanwhile, voice-activated technology gadgets can also provide a medication reminder. While not specifically designed for seniors, these can be used by senior-aged adults. More recently, home-based smart devices have been developed that provide medication reminders. Notably, this can enable the user to be reminded each day to take a specific prescription medication at a specific time of day. Since these reminders can enable senior-aged adults to take daily medications at the right dose and at the right time of day, they can significantly increase medication adherence in seniors.
The Ōmcare Home Health Hub® is an all-in-one platform that is designed specifically for seniors and provides medication alerts while actually storing and dispensing the medication in pre-packaged pouches from the pharmacy, making right med, right time, right person a concern of the past.